

A toothache that fades by morning is easy to ignore. The one that keeps coming back — the zing from cold water that lingers half a minute, the ache that wakes you at 3 a.m., the tooth that suddenly hates being chewed on — that one is usually trying to say something specific.
Very often, it’s saying the pulp inside the tooth is in trouble. The pulp is the living tissue at the tooth’s centre, and when it becomes irreversibly inflamed or infected, a filling can’t fix it. That’s the point where root canal treatment enters the conversation — not as the scary last resort it’s often made out to be, but as the procedure that removes the source of the pain and lets you keep your natural tooth.
This guide walks through the signs you may need a root canal, the signs that point to something else entirely, how the save-it-or-remove-it decision is actually made, and what treatment involves, step by step. If you’re in North York and a tooth has been nagging at you, this is the honest version — including the parts where waiting has real consequences.
Table of Contents
In this article
Inside an Aching Tooth: What the Pulp Is and Why It Hurts
Every tooth has a pulp chamber at its centre, holding the nerve and blood vessels that kept the tooth alive as it developed. Around it sit the hard layers — dentine, then enamel — that are supposed to protect it.
That protection has limits. A deep cavity, a crack, an old large filling, or a hard knock can let bacteria or pressure reach the pulp. The pulp responds the only way it can: it becomes inflamed. But it sits inside a rigid box with almost no room to swell, so inflammation quickly turns into pressure — and pressure on a nerve is pain. That’s why pulp pain has a particular character: it lingers, throbs, and sometimes spreads so you can’t tell which tooth it is.
Two outcomes are possible. If the inflammation is caught while it’s still reversible, the pulp can settle. Once it crosses into irreversible inflammation — or the tissue dies and bacteria take over the space — the pulp can’t recover on its own. Removing it, cleaning the inside of the tooth, and sealing it is what root canal treatment does. The tooth stays; the source of the pain goes.
The Signs That Point to Root Canal Treatment
No single symptom proves a tooth needs a root canal — that’s what the exam and X-ray are for. But these are the signs dentists take seriously, especially in combination:
- Sensitivity to hot or cold that lingers. A quick zing that vanishes is common and often harmless. Sensitivity still there 30 seconds after the coffee or ice water is gone is a classic pulp warning.
- Pain that wakes you at night, or throbbing that starts on its own without anything touching the tooth.
- Pain when you bite or press on the tooth — the tissues around the root tip are inflamed.
- A pimple-like bump on the gum near the tooth that comes and goes. This is usually a drainage point for infection at the root tip — the body coping, not healing.
- Swelling in the gum or face near the tooth.
- A tooth turning darker than its neighbours, sometimes months after a knock — the pulp inside has died.
- A deep cavity, crack, or large old filling on a tooth that’s started to ache.
One pattern deserves its own warning: a tooth that hurt for weeks and then stopped. That can mean the nerve has died, not that the problem has resolved. The infection can continue quietly at the root tip, damaging bone, long after the pain signal switches off. Of all the signs you may need a root canal, the pain that mysteriously disappears is the one people most often misread.
Signs It Might Be Something Else
Honesty cuts both ways: not every toothache is a pulp problem, and part of a good assessment is ruling out the look-alikes:
- A cracked filling or lost restoration can expose sensitive dentine and cause sharp, short pains — a repair, not a root canal.
- Gum disease or food trapped between teeth causes aching and tenderness that can mimic tooth pain.
- Sinus pressure. The roots of the upper back teeth sit close to the sinuses; a bad sinus episode can make several upper teeth ache at once — a giveaway it’s not one tooth’s pulp.
- Grinding at night can leave teeth sore and sensitive in the morning.
- A high filling after recent dental work makes one tooth take the full force of your bite.
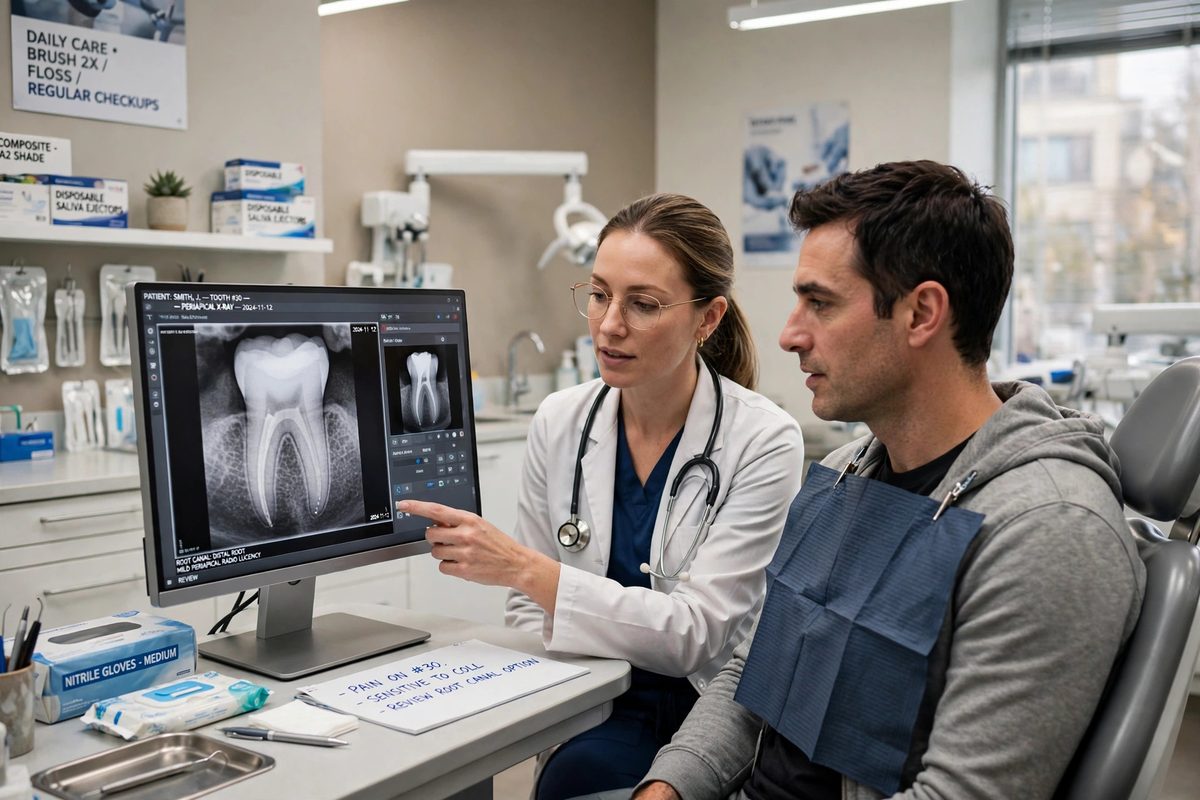
This is why treatment follows diagnosis, not the other way round. Your dentist will test the tooth — tapping, temperature, bite — and take an X-ray to see the root tip and bone. Sometimes the answer is a root canal; sometimes it’s a much smaller fix. What you want is the exam that tells the difference.
Root Canal vs. Extraction: How the Decision Is Actually Made
When the pulp can’t be saved, the choice is usually between saving the tooth with root canal treatment and removing it. Dentists lean toward saving a natural tooth when it’s realistically saveable — nothing chews, feels, or holds the neighbouring teeth in line quite like the original. Here’s how the decision is weighed:
A root canal usually makes sense when the tooth has enough sound structure left, the crack (if there is one) doesn’t run through the root, the bone support is healthy, and the tooth can be properly sealed and crowned afterwards.
Extraction becomes the honest recommendation when the tooth is split or cracked through the root, decay has destroyed too much of it to rebuild, the bone support is badly compromised, or the tooth can’t be sealed reliably — a root canal that can’t be sealed properly isn’t a favour to anyone.
There’s also a middle path people forget: doing nothing for now is itself a decision, and for an infected tooth it’s rarely a neutral one (the next sections cover why). If removal turns out to be the right call, that’s a separate conversation about when extraction is the better option and what replaces the tooth afterwards. Either way, you should hear the reasoning out loud — which option, and why, for your tooth specifically.
What Happens at a Root Canal Appointment, Step by Step
The word patients use most afterwards is “anticlimactic.” The procedure has a fearsome reputation from decades ago; the modern version is methodical and, for most people, comparable to getting a filling. The steps:
- Freezing first. The tooth is numbed with local anaesthesia, and the team confirms you’re numb before anything starts. If you feel something during treatment, you raise a hand — more anaesthetic can always be added.
- Isolation. A small protective sheet (a dental dam) is placed around the tooth to keep it clean and dry.
- Access. A small opening is made through the top of the tooth to reach the pulp chamber.
- Cleaning. The inflamed or infected pulp is removed, and the narrow canals inside the roots are cleaned, shaped, and disinfected — this is the unhurried part of the appointment, and the part that determines how well the tooth settles.
- Sealing. The cleaned canals are filled and sealed so bacteria can’t re-enter.
- Closing up. The tooth is closed with a filling — and, very often, planned for a crown (next section), because a tooth that has lost its pulp is more brittle than it was.
For a full description of how treatment is planned here, see root canal treatment at Vita Dentistry. Most single-rooted teeth are treated in one visit; molars, with their multiple curved canals, sometimes take two. Your dentist will tell you which to expect before you start.
After Treatment: The Crown Question
A root-canal-treated tooth has no living pulp, and it has usually already lost structure to decay or the access opening. It keeps working — but it’s more prone to cracking under chewing forces, especially a back tooth. That’s why a crown is so often the second half of the plan: it wraps the tooth and spreads the bite forces over it. The details are covered in our guide to protecting the tooth with a crown afterwards.
Recovery itself is usually unremarkable. Some tenderness when you bite for a few days is normal as the tissues around the root tip settle — they’d been inflamed, sometimes for a long time. Tenderness that gets worse after the first few days, or swelling that appears, is worth a call. And if your treated tooth had been silent-but-infected, treatment removes the infection source; the bone at the root tip then heals gradually over the following months, which follow-up X-rays can confirm.
What If You Wait? The Honest Risks of Delaying
Teeth with dying or infected pulps don’t heal, and they don’t stay the same either. The realistic paths of waiting:
- The pain escalates. Irreversible pulpitis tends to progress; the 3 a.m. throbbing usually isn’t the worst of it.
- Infection spreads into the bone at the root tip, gradually destroying the bone that holds the tooth — which can turn a saveable tooth into an unsaveable one.
- An abscess can flare, with swelling and fever; facial swelling is a same-day problem, and swelling that affects swallowing or breathing is an emergency-room problem.
- The tooth can crack under normal chewing once it’s weakened, ending the save-it option altogether.
None of this is meant to frighten you into a chair — some monitored situations genuinely can wait a short, planned time, and your dentist will say so if yours is one of them. But “waiting to see” should be a decision made after an exam, with a review point — not a default. The exam is quick; it converts a worry into a plan.
If a tooth has been sending you signals — the lingering sensitivity, the night ache, the bump on the gum — the next step isn’t to decide about a root canal on your own. It’s an assessment: tests, an X-ray, and a straight answer about what’s happening inside the tooth and what your options are. Call Vita Dentistry in North York at (647) 276-0076 to book, and bring your questions. If treatment is recommended, the plan — and what it involves at each visit — will be explained before anything begins.
References
The guidance in this article reflects Canadian dental practice and patient-education resources from the Ontario Dental Association, the Canadian Dental Association and the Royal College of Dental Surgeons of Ontario (RCDSO). Dentists in Ontario are licensed by the RCDSO, and patients can verify a dentist’s registration on the RCDSO website.
Frequently Asked Questions About Root Canals
Does a root canal hurt?
The treatment itself is done with the tooth fully numbed by local anaesthesia — most patients say it felt much like having a filling done. The part that hurts is the condition being treated: an inflamed or infected pulp is genuinely painful, and treatment is what ends it. Afterwards, some tenderness for a few days is common, especially when biting, as the tissues around the root settle. Pain that worsens after a few days instead of easing is a reason to call the clinic.
How many visits does a root canal take?
Often one visit for a front tooth, and one or two for a molar — molars have more canals, and theirs curve. It also depends on how infected the tooth is when treatment starts; occasionally medication is placed inside the tooth and the sealing is finished at a second visit once things have settled. You’ll be told the expected number of visits before treatment begins.
Does the CDCP cover root canals?
Root canal treatment is listed among the services the Canadian Dental Care Plan (CDCP) covers for eligible patients. Eligibility is decided by the federal program first: in general, you must have no access to dental insurance and an adjusted family net income below $90,000, and coverage follows the plan’s fee guide and rules — a co-payment may apply depending on income, so it should never be read as covering the full fee. The official details are on Canada.ca’s CDCP pages. If you’re a CDCP patient, tell the clinic when you book so your coverage can be confirmed before treatment.
Can a root-canal tooth break afterwards?
Yes — it’s one of the main reasons a crown is usually recommended afterwards, particularly on back teeth. A treated tooth no longer has its pulp and has typically lost structure to decay and the treatment itself, so it’s more brittle. A crown spreads chewing forces over the whole tooth. Until the crown is placed, it’s wise to go easy on that tooth — avoid hard foods on it.
When is pulling the tooth honestly the better choice?
When the tooth can’t be reliably saved: a crack running through the root, decay that has destroyed too much structure to rebuild, severe loss of the bone supporting the tooth, or canals that can’t be properly cleaned and sealed. In those cases, keeping the tooth means keeping a source of infection. Your dentist should explain which of these applies to your tooth — and what replacing it would involve — before you decide.
My tooth stopped hurting. Does that mean it’s fine now?
Not necessarily — this is one of the most misleading patterns in dentistry. A tooth can stop hurting because the nerve inside has died, while the infection continues at the root tip, quietly affecting the surrounding bone. A tooth that hurt for weeks and then went silent deserves an exam and an X-ray, not a celebration. Sometimes it really has settled; the X-ray is how you know.
How does the dentist know for sure a root canal is needed?
From a combination of your symptoms and clinical tests: how the tooth responds to cold and to tapping, whether biting on it hurts, and an X-ray showing the root tips and surrounding bone. No single test decides it — the picture comes together from several findings, and your dentist should be able to show you what the X-ray shows and explain why treatment is (or isn’t) recommended.
How long does a root-canal-treated tooth last?
With a proper seal, a protective crown where one is recommended, and normal care, a treated tooth can serve for many years — often as long as its neighbours. What shortens its life is usually new decay at the edges, a crack from unprotected chewing forces, or gum disease around it. Regular checkups let the clinic monitor the tooth, including periodic X-rays of the root tip.

